
Yes! You can use AI to fill out Form OWCP-915, Claim for Medical Reimbursement
Don't type 62 fields by hand. Tell our AI about yourself, or upload a document you already have, and it fills every field in seconds. You check it, then download, print or sign.
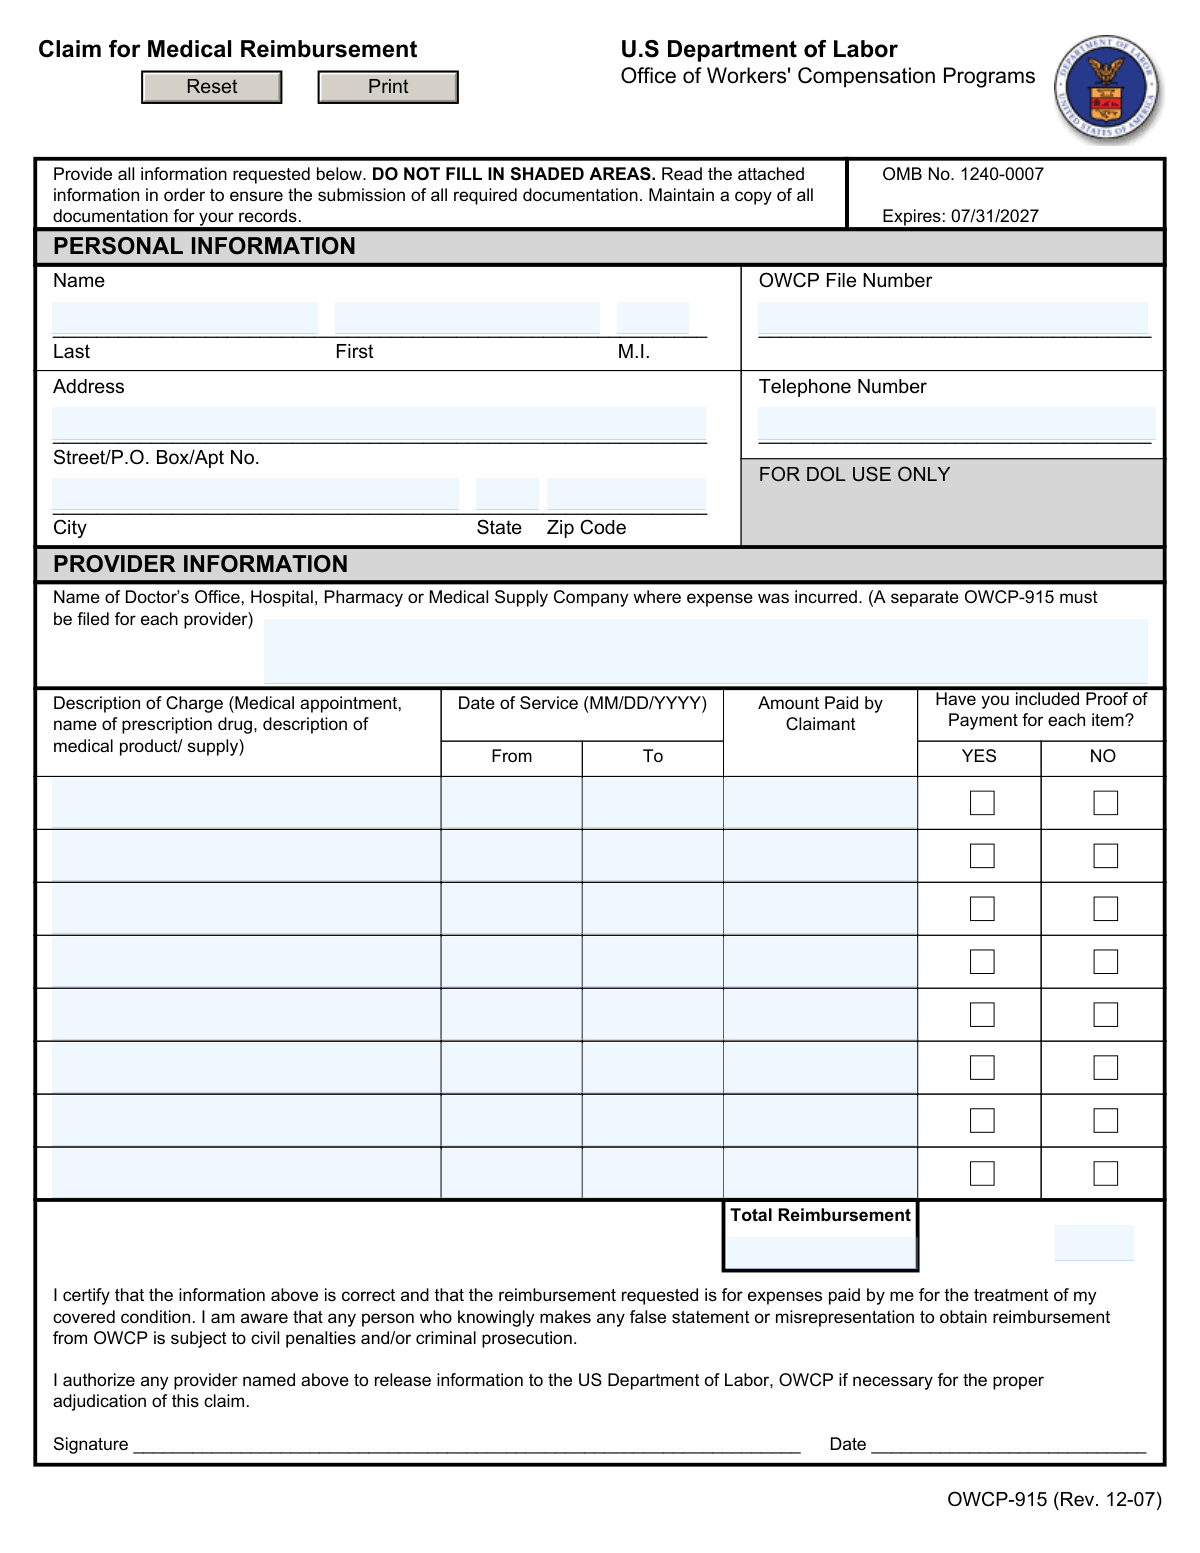
The AI does the filling. You just check it.
No typing into boxes, nothing to install.
What this form asks for
The AI fills all of it, from your answers or your documents.
The AI checks your answers before you download
15 checks built for this form, so a wrong date or a missing answer is caught before anyone else sees it.
Ensures that all shaded areas on the Claim for Medical Reimbursement form are left blank, as these sections are reserved exclusively for the Department of Labor (DOL) use. The AI identifies these areas based on their visual markers and prevents any data from being entered into them. This check is crucial to maintain the integrity of the form submission process and to adhere to the guidelines set by the DOL.
Confirms that the Claim for Medical Reimbursement form is current and has not expired, with a validity date extending until 07/31/2027. The AI cross-references the form's date with the current date to ensure compliance. This validation is essential to prevent the submission of outdated forms, which could result in processing delays or rejections.
Verifies that the personal information section of the Claim for Medical Reimbursement form is fully completed, including the claimant's last name, first name, and middle initial. The AI checks for the presence and correctness of this information to ensure that the claim is associated with the correct individual. This step is vital for the accurate processing of the claim.
Checks that the OWCP File Number is provided on the Claim for Medical Reimbursement form and verifies its accuracy. The AI uses pattern recognition to confirm that the number matches the expected format and is a valid reference. This check is important to link the claim to the correct case file within the Office of Workers' Compensation Programs (OWCP).
Ensures that the address provided on the Claim for Medical Reimbursement form is complete, including the street address, P.O. Box or apartment number, if applicable. The AI assesses the address fields to confirm that no critical components are missing, which is necessary for proper communication and correspondence regarding the claim.
The AI ensures that the city, state, and zip code fields are populated with appropriate data. It checks for the correct format and completeness of the address information. The AI also cross-references the zip code with the city and state to confirm accuracy. This validation helps prevent errors that could delay the processing of the medical reimbursement claim.
And 9 more checks
- Verifies that a valid telephone number is provided.
- Checks that the name of the provider is entered for each medical expense incurred.
- Ensures that the description of charge is specific to the type of medical service, prescription drug, or medical product/supply.
- Confirms that the date of service is indicated in MM/DD/YYYY format and includes both start and end dates if applicable.
- Verifies that the amount paid by the claimant is entered and matches the proof of payment.
- Checks that the claimant has indicated 'YES' or 'NO' for proof of payment for each item listed.
- Calculates and validates the total reimbursement amount requested.
- Ensures that the claimant has read and signed the certification statement to certify the claim.
- Confirms that the current date is entered at the time of signing the form.
Let AI fill out your OWCP-915
No typing. Every field filled in seconds, checked, ready to sign.
How to Fill Out OWCP-915 Online for Free in 2026
What the AI walks you through.
- Visit instafill.ai site and select OWCP-915.
- Enter your personal information accurately.
- Provide details of the medical provider and expenses.
- Attach proof of payment and necessary documentation.
- Sign and date the form electronically.
- Check for accuracy and submit the form.
Common Mistakes in Completing OWCP-915
The ones the AI is built to catch.
Incorrect or incomplete personal information
Failure to provide required documentation
Incorrect calculation of total reimbursement amount
Failure to sign and date the certification statement
Submitting the form after the expiration date
Omitting the Name of Provider for Each Separate Provider
Neglecting to Indicate 'YES' or 'NO' in the Proof of Payment Field for Each Item
Incorrectly Formatting the Date of Service
Using the Incorrect Form for Travel Reimbursement Claims
Failing to Attach Required Documentation for Prescription Medication or Medical Expenses Other Than Prescription Medication
Frequently Asked Questions About OWCP-915
Is it really free for 7 days?
Can I fill other forms too?
How do I cancel?
How does the AI fill out OWCP-915?
What happens to my information?
How complex is OWCP-915 to fill out?
What is the purpose of the Claim for Medical Reimbursement form (OWCP-915)?
What information is required for the Personal Information section?
What documentation is required for prescription medication reimbursement?
What is the role of the provider in the medical reimbursement process?
What happens if the OWCP-1500 or OWCP-04 form is not completed and attached?
What is the process for seeking reimbursement for travel expenses?
What is the estimated time required to complete the Claim for Medical Reimbursement form?
What is the Privacy Act Statement regarding the use of collected information?
What accommodation is available for individuals with disabilities during the claims process?
What is the consequence of failing to provide information regarding medical services or amounts charged?
Get your OWCP-915 filled out by AI
$0 today. Cancel before Nov 1 and you pay nothing.
Other forms like this one
medical forms: Form 8994, Employer Credit for Paid Family and Medical Leave, Form OF-178, Certificate of Medical Examination, Form N-648, Medical Certification for Disability Exceptions, U.S. Coast Guard Form CG-719K, Application for Medical Certificate, The Department of Medical Assistance Services Applied Behavior Analysis Preservice Service Authorization Request Form (Effective Dates of Service 09/01/2025 and after), State of Illinois Department of Children and Family Services Medical Report on an Adult in a Child Care Facility (CFS 602), Carer Payment and Carer Allowance – Medical Report (SA431) for a child under 16 years, Medically Prescribed Treatment (Non-Medication) Form — Provider Treatment Order Form | Office of School Health | School Year 2025–2026, VA Form 10-7959f-2, Foreign Medical Program (FMP) Claim Cover Sheet, Department of Medical Assistance Services Applied Behavior Analysis (97155, Et al.) Initial Service Authorization Request Form, Applied Behavior Analysis Concurrent Service Authorization Request Form (CPT Codes 97153, 97154, 97155, 97156, 97157, 97158, 0373T) – Virginia Department of Medical Assistance Services, Department of Medical Assistance Services Enhanced Services Individual Service Plan (ISP) Template, Form DS-1843, Medical History and Examination for Individuals Age 12 and Older, Scheduled Medical Leave of Absence (MLOA) - BLET 13, Admissions Application, School of Diagnostic Imaging, Mills-Peninsula Medical Center, Albany Medical Center 2024 Benefits Guide, Form BWC-1141, Request for Medical Information, VA Form 21P-8416, Medical Expense Report, Medicare Enrollment Application for Durable Medical Equipment, Prosthetics, Orthotics, and Supplies (DMEPOS) Suppliers, CMS-855S, Form HFS 2243, Provider Enrollment Application Illinois Medical Assistance Program
OWCP forms: Form OWCP-5a, Work Capacity Evaluation, Form OWCP-5c, Work Capacity Evaluation
medical claim forms: VA Form 10-7959f-2, Foreign Medical Program (FMP) Claim Cover Sheet, Standard Health Insurance Claim Form - Part B, DD Form 2642, TRICARE DoD/CHAMPUS Medical Claim Patient's Request for Medical Payment, Cigna Medical Claim Form, Medical Benefits – Claim Instructions and Request
VA medical forms: Form 8994, Employer Credit for Paid Family and Medical Leave, Form OF-178, Certificate of Medical Examination, Form N-648, Medical Certification for Disability Exceptions, U.S. Coast Guard Form CG-719K, Application for Medical Certificate, The Department of Medical Assistance Services Applied Behavior Analysis Preservice Service Authorization Request Form (Effective Dates of Service 09/01/2025 and after), State of Illinois Department of Children and Family Services Medical Report on an Adult in a Child Care Facility (CFS 602), Carer Payment and Carer Allowance – Medical Report (SA431) for a child under 16 years, Medically Prescribed Treatment (Non-Medication) Form — Provider Treatment Order Form | Office of School Health | School Year 2025–2026, VA Form 10-7959f-2, Foreign Medical Program (FMP) Claim Cover Sheet, Department of Medical Assistance Services Applied Behavior Analysis (97155, Et al.) Initial Service Authorization Request Form, Applied Behavior Analysis Concurrent Service Authorization Request Form (CPT Codes 97153, 97154, 97155, 97156, 97157, 97158, 0373T) – Virginia Department of Medical Assistance Services, Department of Medical Assistance Services Enhanced Services Individual Service Plan (ISP) Template, Form DS-1843, Medical History and Examination for Individuals Age 12 and Older, Scheduled Medical Leave of Absence (MLOA) - BLET 13, Admissions Application, School of Diagnostic Imaging, Mills-Peninsula Medical Center, Albany Medical Center 2024 Benefits Guide, Form BWC-1141, Request for Medical Information, VA Form 21P-8416, Medical Expense Report, Medicare Enrollment Application for Durable Medical Equipment, Prosthetics, Orthotics, and Supplies (DMEPOS) Suppliers, CMS-855S, Form HFS 2243, Provider Enrollment Application Illinois Medical Assistance Program
VA claim forms: Form 8862, Information To Claim Certain Credits, Form CA-7, Claim for Compensation, Form CA-5, Claim for Compensation, Form SC-100, Plaintiff's Claim and ORDER to Go to Small Claims Court, Form 20-0995, Decision Review Request: Supplemental Claim, Form 104, List of Creditors 20 Largest Unsecured Claims, Form 941-X (Rev. April 2023), Adjusted Employer’s QUARTERLY Federal Tax Return or Claim for Refund, Judicial Council of California Form SC-104, Proof of Service (Small Claims), Immigration and Refugee Board of Canada (IRB) – Refugee Protection Division (RPD) Basis of Claim Form (for persons claiming refugee protection in Canada) (RPD.02.01), SC-108, Request to Correct or Cancel Judgment and Answer (Small Claims), Judicial Council of California Form SC-105, Request for Court Order and Answer (Small Claims), SC-120, Defendant’s Claim and ORDER to Go to Small Claims Court (Small Claims), Judicial Council of California Form SC-104, Proof of Service (Small Claims), Continental American Insurance Company (CAIC) / Aflac Group Critical Illness Claim Form (with Attending Physician’s Statement, HIPAA Authorization to Obtain Information, and Electronic Funds Transaction Authorization), Judicial Council of California Form SC-108, Request to Correct or Cancel Judgment and Answer (Small Claims), SC-105, Request for Court Order and Answer (Small Claims), Judicial Council of California Form SC-120, Defendant’s Claim and ORDER to Go to Small Claims Court (Small Claims), Small Claim and Notice of Small Claim (ORS 46.425) (OJD Official) (Jan 2026), VA Form 21-4138, Statement in Support of Claim, Form SSA-795, Statement of Claimant or Other Person
Medi-Cal forms: Form 8994, Employer Credit for Paid Family and Medical Leave, Form OF-178, Certificate of Medical Examination, Form N-648, Medical Certification for Disability Exceptions, U.S. Coast Guard Form CG-719K, Application for Medical Certificate, The Department of Medical Assistance Services Applied Behavior Analysis Preservice Service Authorization Request Form (Effective Dates of Service 09/01/2025 and after), State of Illinois Department of Children and Family Services Medical Report on an Adult in a Child Care Facility (CFS 602), Carer Payment and Carer Allowance – Medical Report (SA431) for a child under 16 years, Medically Prescribed Treatment (Non-Medication) Form — Provider Treatment Order Form | Office of School Health | School Year 2025–2026, VA Form 10-7959f-2, Foreign Medical Program (FMP) Claim Cover Sheet, ABA Authorization Request (Medi-Cal) – Initial and Concurrent Requests, Department of Medical Assistance Services Applied Behavior Analysis (97155, Et al.) Initial Service Authorization Request Form, Applied Behavior Analysis Concurrent Service Authorization Request Form (CPT Codes 97153, 97154, 97155, 97156, 97157, 97158, 0373T) – Virginia Department of Medical Assistance Services, Department of Medical Assistance Services Enhanced Services Individual Service Plan (ISP) Template, Form DS-1843, Medical History and Examination for Individuals Age 12 and Older, Scheduled Medical Leave of Absence (MLOA) - BLET 13, Admissions Application, School of Diagnostic Imaging, Mills-Peninsula Medical Center, Albany Medical Center 2024 Benefits Guide, Form BWC-1141, Request for Medical Information, VA Form 21P-8416, Medical Expense Report, Medicare Enrollment Application for Durable Medical Equipment, Prosthetics, Orthotics, and Supplies (DMEPOS) Suppliers, CMS-855S
Let AI fill out your OWCP-915
Your trial starts once a card is added. You pay nothing before Nov 1.
Our AI already knows this form, all 62 fields of it. Skip the typing: tell it about yourself, or upload what you have, and it fills the whole form in seconds.
- AI fills every field on the form, checkboxes included
- No typing into boxes: answer a few questions, or upload a document you already have, an old copy of this form, a photo of a document
- The AI checks the answers; you review and change anything before you download
- Download the finished PDF, print it, or sign it online
- Encrypted, and never used to train AI
Cancel before Nov 1 and you pay nothing.
A card is needed to start the trial. Cancel in two clicks from your account.
Terms · Privacy