
Yes! You can use AI to fill out Meritain Health Claim Form (Health Claim Form)
Don't type 227 fields by hand. Tell our AI about yourself, or upload your insurance card, and it fills every field in seconds. You check it, then download, print or sign.
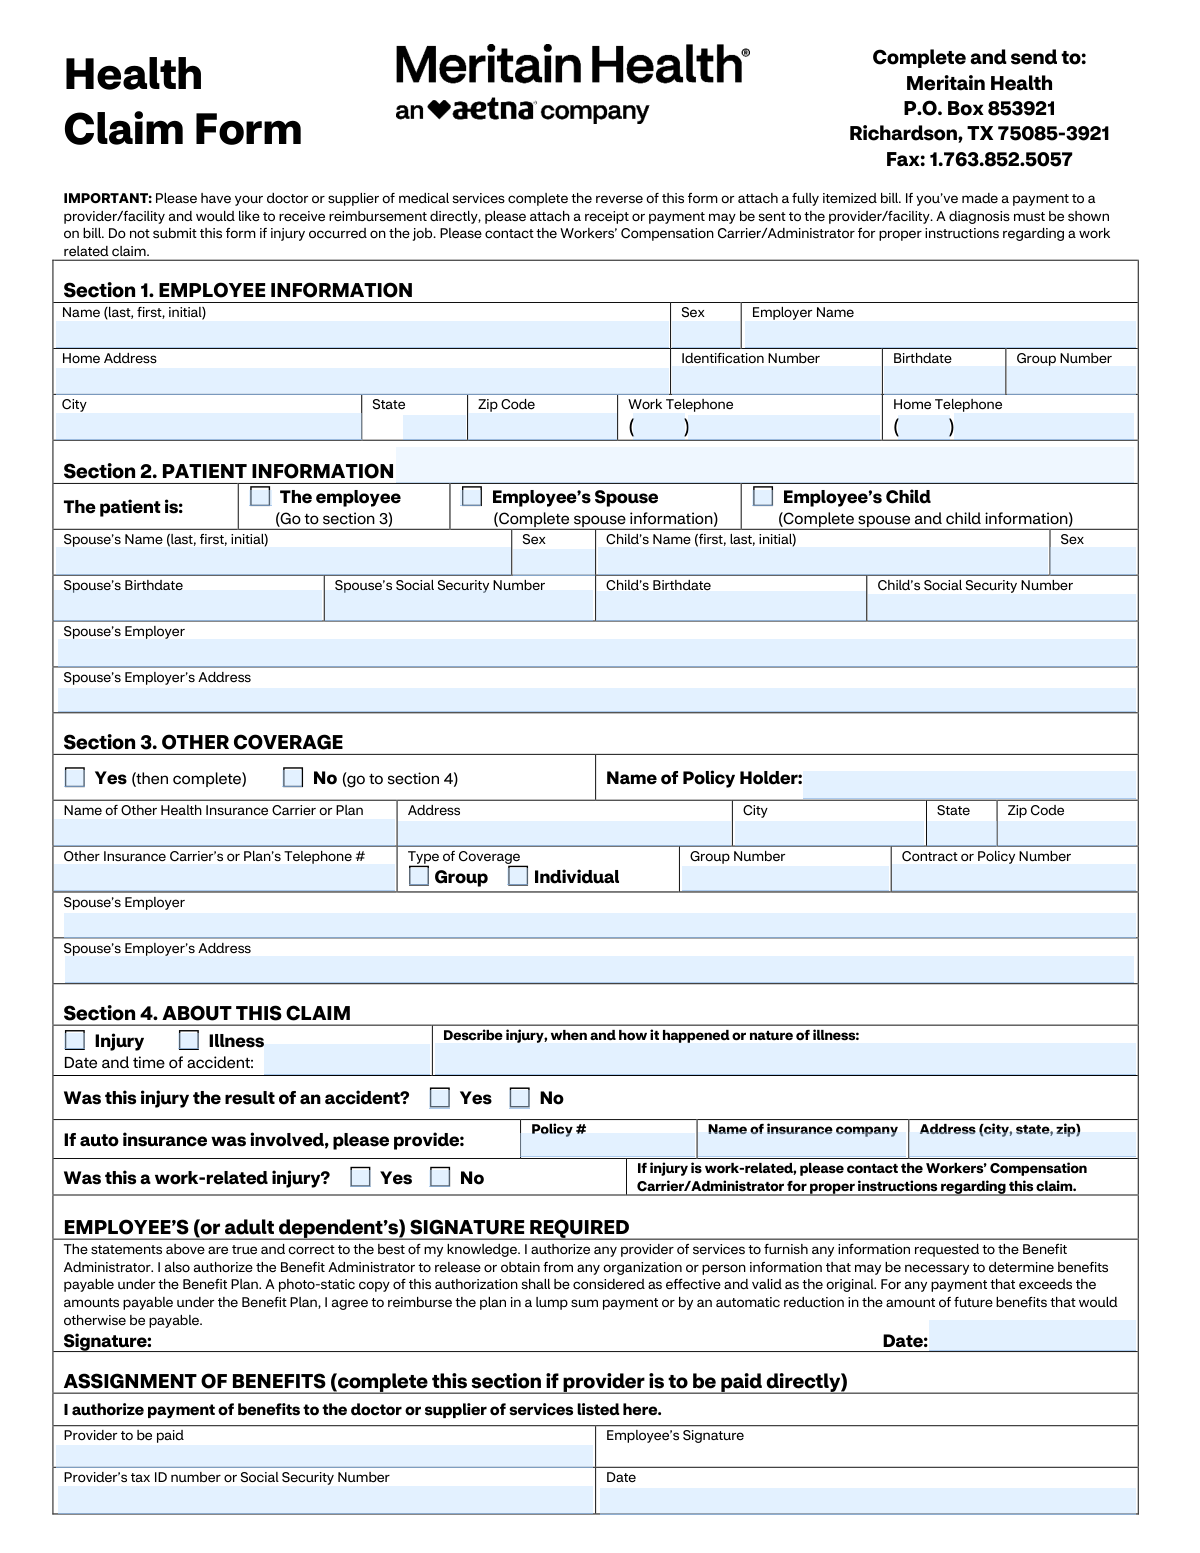
The AI does the filling. You just check it.
No typing into boxes, nothing to install.
What this form asks for
The AI fills all of it, from your answers or your documents.
The AI checks your answers before you download
16 checks built for this form, so a wrong date or a missing answer is caught before anyone else sees it.
Validates that the core employee fields are present: Employee Name, Sex, Employer Name, Identification Number, Birthdate, Group Number, and full home address (street/city/state/zip). These fields are required to match the claim to the correct member and plan and to route correspondence. If any are missing, the submission should be rejected or pended as “incomplete member information” and the user prompted to supply the missing fields.
Checks that Employee Birthdate is a valid date in an accepted format (e.g., MM/DD/YYYY) and is not in the future. Also validates plausibility (e.g., age between 0 and 120) to catch transposed digits and data-entry errors. If validation fails, the claim should be pended because eligibility and dependent rules often rely on accurate DOB.
Ensures address blocks (Employee Home Address, Patient Address, Spouse Employer Address, Other Insurance Address, Physician Address) contain minimally required components: street, city, state, and ZIP where applicable. State must be a 2-letter US abbreviation and ZIP must be 5 digits (optionally ZIP+4). If invalid, the system should flag the record for correction because payments, EOBs, and coordination-of-benefits letters may be undeliverable.
Validates that phone numbers are provided in the expected structure where split fields exist (area code and main number) and that each part is numeric with correct lengths (3-digit area code, 7-digit main). This applies to Employee Work/Home phones, Other Insurance phone, and Physician phone. If invalid, the submission should be accepted with a warning or pended depending on business rules, since missing/invalid contact info can delay claim resolution.
Checks that exactly one patient identity checkbox is selected: employee, spouse, or child. Based on the selection, enforces conditional requirements: if spouse is patient, spouse fields (name/sex/DOB/SSN) must be completed; if child is patient, both spouse fields (as indicated by the form) and child fields (name/sex/DOB/SSN) must be completed. If the selection is missing, multiple selected, or dependent fields are incomplete, the claim should be rejected/pended because the patient cannot be unambiguously identified.
Validates that SSNs (Spouse SSN, Child SSN, and any field allowing SSN as provider identifier) are 9 digits and not obviously invalid patterns (e.g., all zeros, 123456789). This reduces downstream eligibility mismatches and prevents storing malformed identifiers. If invalid, the system should block submission or require correction because SSN is used for identification and coordination of benefits in some workflows.
And 10 more checks
- Other coverage Yes/No selection is mutually exclusive and conditionally requires policy details
- Other coverage type selection (Group vs Individual) and related field logic
- Claim reason selection (Injury vs Illness) is mutually exclusive and drives date requirements
- Accident confirmation consistency with claim reason and accident details
- Auto insurance fields required when auto involvement is indicated by narrative/policy entry
- Work-related injury gating (must not be submitted as health claim if work-related)
- Signature and signature date presence and chronology (employee/adult dependent)
- Assignment of Benefits (AOB) conditional requirements
- Provider identifier (Tax ID/SSN) format and exclusivity
- Clinical/service line integrity: dates, codes, and charges consistency
Let AI fill out your Meritain Health Claim Form
No typing. Every field filled in seconds, checked, ready to sign.
How to Fill Out Meritain Health Claim Form Online for Free in 2026
What the AI walks you through.
- Go to Instafill.ai and upload the Meritain Health Claim Form (or select it from the form library) and add any supporting documents such as itemized bills and receipts.
- Enter employee information (name, sex, employer, ID number, birthdate, group number, address, and phone numbers).
- Complete patient information by selecting whether the patient is the employee, spouse, or child, and provide spouse/child details if applicable (names, birthdates, SSNs, employer information).
- Fill out other coverage details (if any), including other insurer name, policyholder, plan type (group/individual), group/policy numbers, and contact information.
- Provide claim details (injury vs. illness, accident date/time, description, auto insurance information if applicable, and confirm whether the injury is work-related).
- Review and e-sign the employee/adult dependent authorization and complete the Assignment of Benefits section if you want the provider paid directly (provider name, tax ID/SSN, dates).
- Have the doctor/supplier complete the provider section (diagnosis, treatment dates, procedure codes, charges, signature) or attach a fully itemized bill, then submit to Meritain Health via mail or fax as listed on the form.
Common Mistakes in Completing Meritain Health Claim Form
The ones the AI is built to catch.
Submitting the claim without an itemized bill and diagnosis
Filling the wrong patient path (employee vs spouse vs child)
Missing or incorrect employee identifiers (ID number and group number)
Phone number and address formatting errors
Not completing the 'Other Coverage' section correctly (COB mistakes)
Work-related injury confusion (submitting when it should be Workers’ Comp)
Accident/auto insurance details left blank or inconsistent
Signature/date missing or signed by the wrong person
Assignment of Benefits completed incorrectly (provider pay-to errors)
Provider/doctor section incomplete or not filled out by the provider
Coding and date-of-service errors (ICD-10/CPT/place of service/From-To)
Frequently Asked Questions About Meritain Health Claim Form
Is it really free for 7 days?
Can I fill other forms too?
How do I cancel?
How does the AI fill out Meritain Health Claim Form?
What happens to my information?
How complex is Meritain Health Claim Form to fill out?
What is this Health Claim Form used for?
Who should fill out this form—me or my doctor?
Where do I send the completed claim form?
What documents do I need to attach to the form?
Does the bill need to include a diagnosis?
Should I use this form for a work-related injury?
How do I complete Section 2 if the patient is my spouse or child?
What should I do in Section 3 (Other Coverage) if the patient has another insurance plan?
How do I fill out Section 4 if the claim involves an accident or auto insurance?
What is the “Assignment of Benefits” section and when should I complete it?
What information does the provider need to complete on the reverse side?
What are “place of service” codes on the provider section?
How long does it take to process this claim after I submit it?
Can AI tools help me fill out this Meritain Health claim form?
How do I fill out this form online using Instafill.ai, and what if my PDF isn’t fillable?
Get your Meritain Health Claim Form filled out by AI
$0 today. Cancel before Nov 17 and you pay nothing.
Other forms like this one
VA forms: Ankle Conditions Disability Benefits Questionnaire, Shoulder and Arm Conditions Disability Benefits Questionnaire, VA Form 10-7959f-2, Foreign Medical Program (FMP) Claim Cover Sheet, VA Form 21-0781a, Statement in Support of Claim for Service Connection for Post-Traumatic Stress Disorder (PTSD) Secondary to Personal Assault, VA Form 21-0788, Information Regarding Apportionment of Beneficiary's Award, VA Form 21-4138, Statement in Support of Claim, Wrist Conditions Disability Benefits Questionnaire (DBQ), VA Form 21-0781, Statement in Support of Claimed Mental Health Disorder(s) Due to an In-Service Traumatic Event(s), VA Form 29-357, Claim for Disability Insurance Benefits (Government Life Insurance), VA Form 21-686c, Declaration of Status of Dependents, Form #170, Voluntary Account Withdrawal Request Form, Meritain Health Claim Form (Health Claim Form), Form 4852, Substitute for Form W-2 or 1099-R, PSA Form/K/II/052025 - Formulir Pembukaan Rekening / Account Opening Form, Form WH-347, Davis-Bacon and Related Acts Weekly Certified Payroll Form, Vanguard IRA Distribution Kit (including IRA Distribution Form RRDFT and Form W-4R), Davis-Bacon and Related Acts Weekly Certified Payroll Form (Form WH-347), Uniform Underwriting and Transmittal Summary (Fannie Mae Form 1008 / Freddie Mac Form 1077), Form 5385BSP, Behavioral Health Utilization Management Applied Behavioral Analysis (ABA) Initial Request Form, Applied Behavioral Analysis (ABA) Authorization Form, Louisiana Health Connect (BRO-DP-ABA FORM-0822)
Meritain Health forms: Meritain Health Claim Form (Health Claim Form)
HR forms: U.S. Equal Employment Opportunity Commission (EEOC) Form 453, Recommendation for Recognition, U.S. Equal Employment Opportunity Commission (EEOC) Form 453, Recommendation for Recognition, EzB – Erklärung zum Beschäftigungsverhältnis (02/2024), New York State Employment Application Form, A Place for Mom 401(k) Plan Request for Rollover Contribution Form, ADP Compensation and Fee Disclosure Statement, ADP Leave Management Application for Leave of Absence, ADP Retirement Services Beneficiary Designation Form, ADP Year-End Seminar Handout Manual, AeroVironment Profit Sharing and Salary Deferral 401(k) Plan In-Service Withdrawal Form, Albany Medical Center 2024 Benefits Guide, Authorization Agreement for Direct Deposit, Beneficiary Designation 401(k) Plan, ENVIRONMENTAL MONITORING LABORATORY, LLC Employment Application, Earnings and Deductions Quick Reference, Employee Direct Deposit Banking Authorization Form (RUN Powered by ADP®), Employee’s Frequently Asked Questions: Leave of Absence, Form 2938, Hardship Withdrawal Request, Form I-9, Employment Eligibility Verification, Group Life Conversion FAQ Sheet
VA claim forms: Form OWCP-915, Claim for Medical Reimbursement, Form 8862, Information To Claim Certain Credits, Form CA-7, Claim for Compensation, Form CA-5, Claim for Compensation, Form SC-100, Plaintiff's Claim and ORDER to Go to Small Claims Court, Form 20-0995, Decision Review Request: Supplemental Claim, Form 104, List of Creditors 20 Largest Unsecured Claims, Form 941-X (Rev. April 2023), Adjusted Employer’s QUARTERLY Federal Tax Return or Claim for Refund, Judicial Council of California Form SC-104, Proof of Service (Small Claims), Immigration and Refugee Board of Canada (IRB) – Refugee Protection Division (RPD) Basis of Claim Form (for persons claiming refugee protection in Canada) (RPD.02.01), SC-108, Request to Correct or Cancel Judgment and Answer (Small Claims), Judicial Council of California Form SC-105, Request for Court Order and Answer (Small Claims), SC-120, Defendant’s Claim and ORDER to Go to Small Claims Court (Small Claims), Judicial Council of California Form SC-104, Proof of Service (Small Claims), Continental American Insurance Company (CAIC) / Aflac Group Critical Illness Claim Form (with Attending Physician’s Statement, HIPAA Authorization to Obtain Information, and Electronic Funds Transaction Authorization), Judicial Council of California Form SC-108, Request to Correct or Cancel Judgment and Answer (Small Claims), SC-105, Request for Court Order and Answer (Small Claims), Judicial Council of California Form SC-120, Defendant’s Claim and ORDER to Go to Small Claims Court (Small Claims), Small Claim and Notice of Small Claim (ORS 46.425) (OJD Official) (Jan 2026), VA Form 21-4138, Statement in Support of Claim
health forms: Form 1095-A, Health Insurance Marketplace Statement, Form 8889, Health Savings Accounts, Form WH-380-E, Certification of Health Care Provider, Form 7206, Self-Employed Health Ins. Ded., Form 8885, Health Coverage Tax Credit, Form WH-380-F, Certification of Health Care Provider, Form 1095-C, Employer-Provided Health Insurance Offer and Coverage, Form 1095-B, Health Coverage, Form I-905, Application for Authorization to Issue Certification for Health Care Workers, Form BHVH, Outpatient Behavioral Health – ABA Treatment Request, Form SHA, Separation Health Assessment, DHS-6696-ENG, Minnesota Health Care Programs Application (MNsure/DHS), Geisinger Health Plan Behavioral Health Professional Services Questionnaire, Priority Health Small Group Renewal Decision Form, Form CH-006: PA-BH-Res-PCS, Oregon Behavioral Health Support Program Plan of Care Authorization (Plan of Care Request for Behavioral Health Residential or Personal Care Services), Form 7206 (2025), Self-Employed Health Insurance Deduction, HIPAA Authorization Form, Authorization for the Release of Protected Health Information, Prior Authorization (PA) Request Form – Adult Palliative Care (Alameda Alliance for Health), Medicare Enrolment Application (Australia) – Enrol in Medicare, Re-enrol/Extend Eligibility, Enrol a Newborn, and Register for My Health Record, Alameda Alliance for Health Prior Authorization (PA) Request Form – Adult Palliative Care
health claim forms: Form AI-346, Gastos Médicos Mayores Informe Médico, Meritain Health Claim Form (Health Claim Form), CMS-1500 (02-12), Health Insurance Claim Form (NUCC Approved) (OMB 0938-1197), VA Form 21-0781, Statement in Support of Claimed Mental Health Disorder(s) Due to an In-Service Traumatic Event(s), VA Form 21-0781, Statement in Support of Claimed Mental Health Disorder(s) Due to an In-Service Traumatic Event(s), Standard Health Insurance Claim Form - Part B, CMS-1500 Health Insurance Claim Form (OMB-0938-0999), Ontario Blue Cross Extended Health Care Benefit Claim Form, Claim for Commonwealth Seniors Health Card, Form SA296, Claim for a Commonwealth Seniors Health Card
Let AI fill out your Meritain Health Claim Form
Your trial starts once a card is added. You pay nothing before Nov 17.
Your bank declined that card, so the trial did not start and nothing was charged. Please try another card.
Our AI already knows this form, all 227 fields of it. Skip the typing: tell it about yourself, or upload what you have, and it fills the whole form in seconds.
- AI fills every field on both pages, checkboxes included
- No typing into boxes: answer a few questions, or upload your insurance card, an old copy of this form, a photo of a document
- The AI checks the answers; you review and change anything before you download
- Download the finished PDF, print it, or sign it online
- Encrypted, and never used to train AI
Cancel before Nov 17 and you pay nothing.
A card is needed to start the trial. We check it with a $19.99 hold that is released right away. Cancel in two clicks from your account.
Terms · Privacy